

Vitamin B12 After 50: Why Absorption Drops, Deficiency Signs and Best Forms
After age 50, vitamin B12 deficiency becomes surprisingly common — and surprisingly easy to miss. The National Institutes of Health (NIH) reports that deficiency affects between 3% and 43% of older adults, depending on how it is measured. The reason is not usually that older adults eat too little B12. It is that their bodies…
After age 50, vitamin B12 deficiency becomes surprisingly common — and surprisingly easy to miss. The National Institutes of Health (NIH) reports that deficiency affects between 3% and 43% of older adults, depending on how it is measured. The reason is not usually that older adults eat too little B12. It is that their bodies absorb less of it: the stomach makes less acid, and a protein called intrinsic factor, which B12 needs to be absorbed, can decline with age. The good news is that B12 deficiency is usually simple to test for and straightforward to treat — if it is caught early. This guide explains why absorption drops after 50, the early signs that show up first, who is most at risk, how testing works, and which food and supplement forms are actually worth your money.
Important: This article is general information only — not medical advice. Vitamin B12 affects your blood, nerves and brain, so talk to your doctor or pharmacist before starting a supplement, changing a dose, or stopping a prescribed medicine. If you have symptoms such as numbness, balance problems or memory changes, get checked promptly: nerve damage from untreated deficiency can become permanent.
Key Takeaways
- Adults need 2.4 micrograms (mcg) of vitamin B12 a day, but after 50 the NIH recommends getting most of it from fortified foods or supplements, because absorption from ordinary food falls.
- The earliest signs are usually fatigue, brain fog, tingling in the hands or feet, a sore tongue and pale skin — and they can appear so gradually that they are mistaken for normal aging.
- The biggest risk factors are age over 50, low stomach acid, pernicious anemia, stomach or weight-loss surgery, digestive conditions such as celiac or Crohn’s disease, a vegan or strict vegetarian diet, and long-term use of metformin or acid-reducing medicines.
- A blood B12 test plus, when results are borderline, a methylmalonic acid (MMA) test is how doctors confirm deficiency.
- There is no good evidence that one supplement form (methylcobalamin vs cyanocobalamin) is absorbed better than another. Dose, consistency and the right route for your situation matter far more than the form on the label.
What Vitamin B12 Does — and Why It Matters More After 50
Vitamin B12, also called cobalamin, is a water-soluble vitamin with three main jobs. It helps make healthy red blood cells, it keeps the nervous system working properly, and it helps make DNA, the genetic material in every cell. When B12 runs low, the body can develop megaloblastic anemia — a condition in which red blood cells are larger than normal and cannot carry oxygen efficiently — and it can damage the nervous system, sometimes even when there is no anemia at all.
That is why B12 matters more after 50 than it did at 30. Your body stores roughly 1 to 5 milligrams of B12 in the liver, which is 1,000 to 2,000 times the amount you eat in a day. Because of that large store, deficiency can take years to show up. By the time symptoms appear, the problem may already have been building quietly for a long time. And because the early symptoms — tiredness, forgetfulness, a little unsteadiness — overlap with what many people expect from aging, they are easy to dismiss.
The stakes are real but manageable. Treated early, most B12 deficiency improves. Left untreated, it can lead to lasting nerve damage. That is the whole case for knowing the signs and getting tested: a simple blood test can catch something that is otherwise easy to miss for years.
Why Absorption Drops After 50
Eating enough B12 and absorbing enough B12 are two different things, and after 50 the second half of that equation is where the trouble starts. B12 in food is bound to protein. To free it, your stomach must produce enough acid and an enzyme called pepsin. Then the freed B12 must attach to intrinsic factor, a protein made by the stomach lining, before it can be absorbed in the small intestine. Age can weaken every step of that chain.
Less stomach acid (atrophic gastritis). Many older adults develop atrophic gastritis, a thinning of the stomach lining that reduces acid production. The NIH notes that many older adults do not have enough hydrochloric acid in their stomach to absorb the B12 that is naturally present in food. This is why the NIH advises people over 50 to get most of their B12 from fortified foods or dietary supplements — the B12 in those products is already in its free form and does not need stomach acid to be released.
Less intrinsic factor. The stomach cells that make intrinsic factor can also decline with age, and in pernicious anemia — an autoimmune condition — the body attacks those cells directly. Without intrinsic factor, B12 from food and from ordinary oral supplements is poorly absorbed, no matter how much you swallow.
Medicines that lower acid. Long-term use of proton pump inhibitors (PPIs) such as omeprazole and lansoprazole, and H2 blockers such as famotidine, reduces stomach acid and can lower B12 levels over time. Metformin, widely used for type 2 diabetes, is also known to lower B12 levels in some people. If you take any of these medicines long term, B12 is worth discussing at your next check-up — never stop a prescribed medicine on your own to “fix” B12.
Surgery and digestive conditions. Weight-loss (bariatric) surgery, stomach surgery, celiac disease and Crohn’s disease can all reduce the gut’s ability to absorb B12. People in these groups often need lifelong monitoring and sometimes injections rather than pills. All of these conditions affect gut health, and they are a reminder that absorption — not just diet — is the issue after 50.
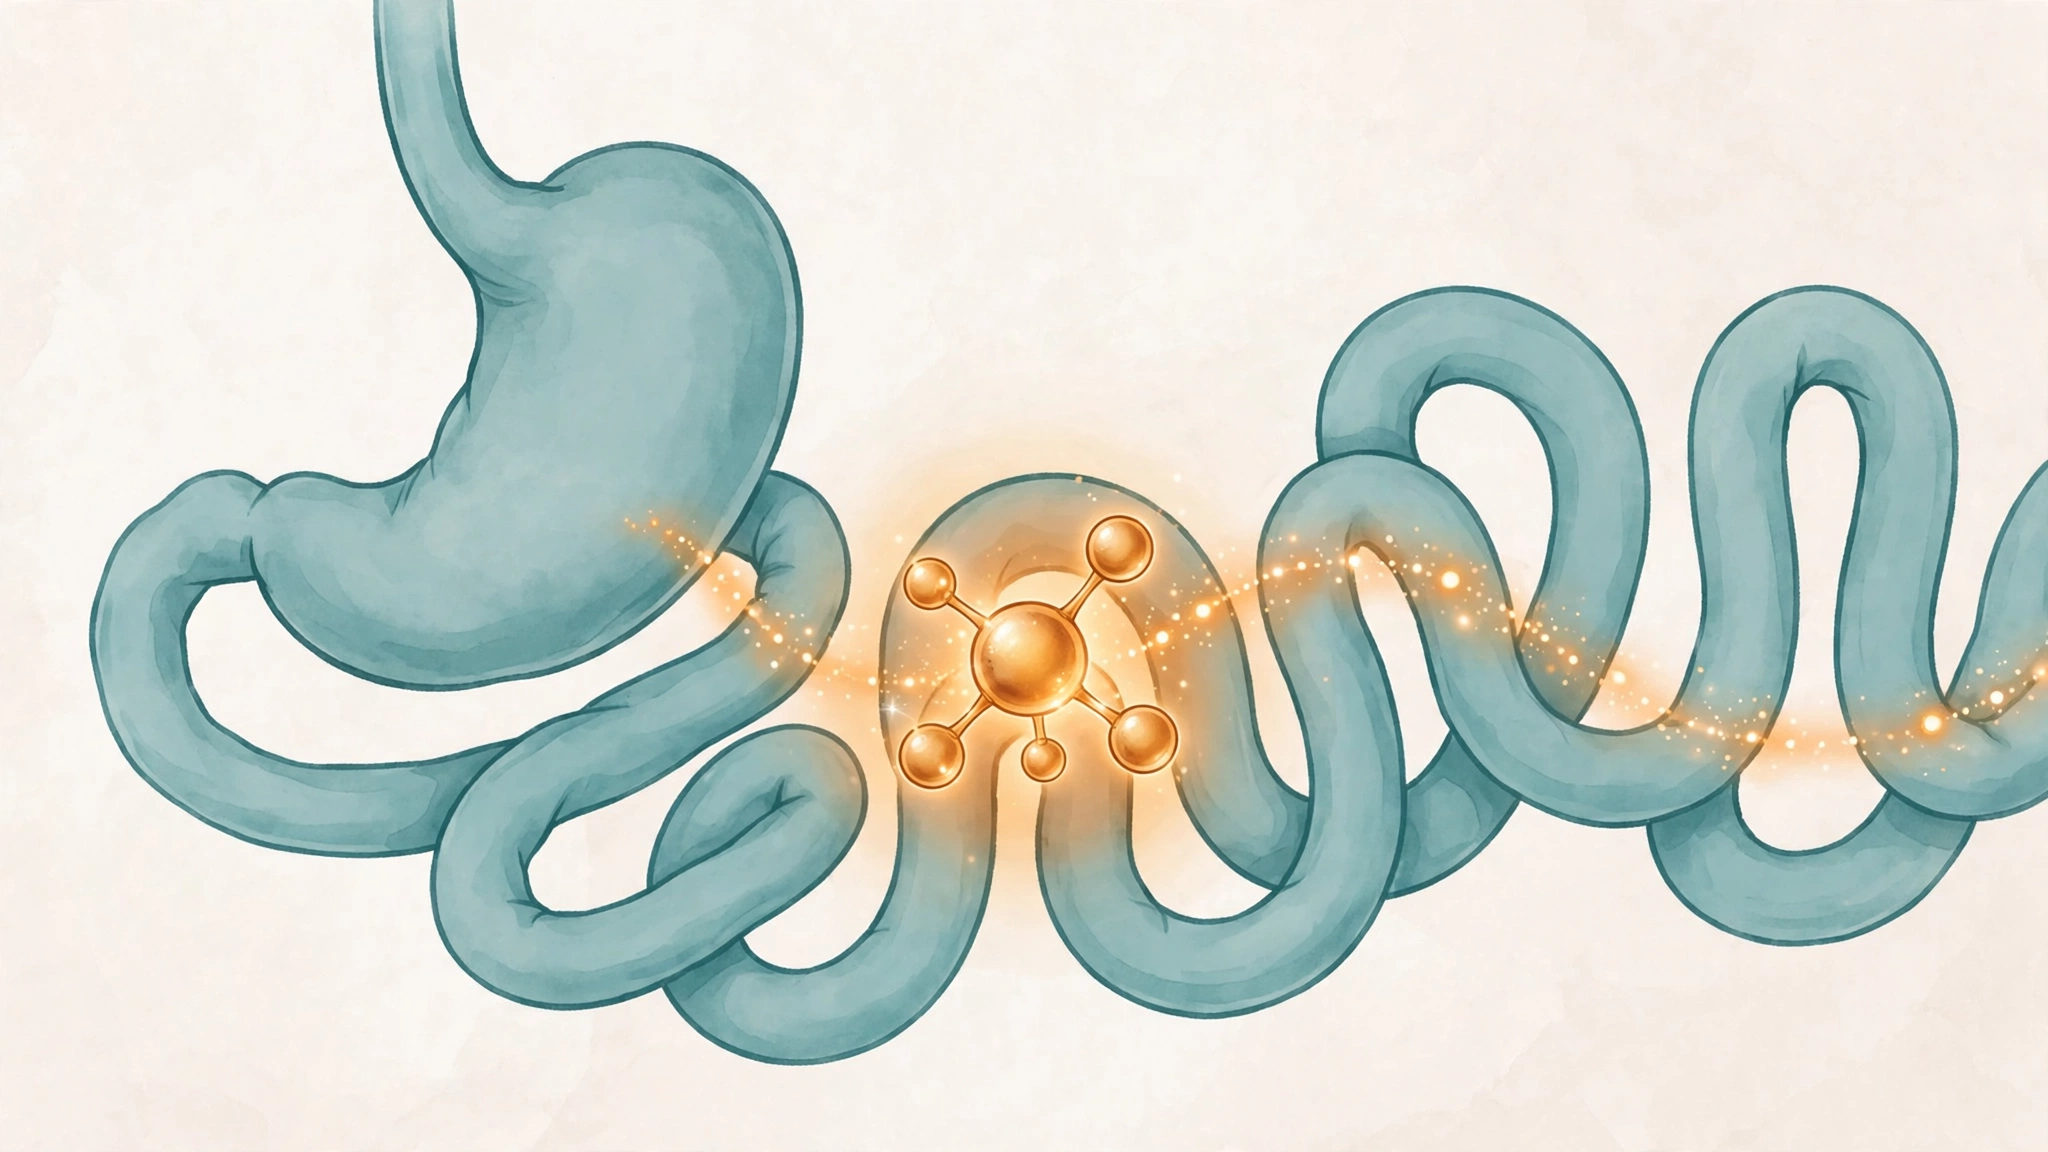
Absorption after 50, at a glance
| Step | What happens | What can go wrong after 50 |
|---|---|---|
| Step 1 — Food is eaten | B12 is bound to protein in meat, fish, eggs and dairy. | Diet may change, but this step usually still works. |
| Step 2 — Stomach acid frees B12 | Acid and pepsin release B12 from food protein. | Less acid (atrophic gastritis, PPIs, H2 blockers) means less B12 is freed. |
| Step 3 — Intrinsic factor binds B12 | The stomach makes intrinsic factor, which carries B12 to the small intestine. | Less intrinsic factor with age; absent in pernicious anemia. |
| Step 4 — Small intestine absorbs B12 | B12 is absorbed into the blood. | Surgery, celiac or Crohn’s disease can reduce absorption. |
| The workaround | Fortified foods and supplements provide B12 already in free form. | The NIH recommends this route for people over 50. |
The Early Signs That Show Up First
B12 deficiency rarely announces itself loudly. The earliest signs are subtle, slow and easy to blame on stress, poor sleep or simply getting older. That is exactly why they are worth knowing by name. If several of these are new or persistent, they deserve a conversation with your doctor — not a self-diagnosis and not a supplement started in the dark.
1. Fatigue and weakness
The most common early sign. Low B12 can cause megaloblastic anemia, so less oxygen reaches your muscles and brain. You may feel tired even after a full night’s sleep, feel weak climbing stairs, or get short of breath during ordinary activity.
2. Brain fog and memory problems
Difficulty concentrating, forgetfulness and mental sluggishness are common. Many people — and their families — mistake this for early dementia. That is a serious mistake to avoid in both directions: B12 deficiency can mimic dementia, and it is treatable, but B12 supplements have not been shown to prevent or treat dementia or Alzheimer’s disease in people whose B12 is already normal. Only a proper evaluation can tell the two apart.
3. Tingling or numbness in the hands or feet
A pins-and-needles feeling, or numbness that comes and goes, is one of the most important warning signs because it can signal nerve involvement. Nerve symptoms can occur even without anemia, and they can become permanent if deficiency goes untreated for too long. Never ignore persistent tingling.
4. Pale or slightly yellowish skin
Fewer healthy red blood cells can make the skin look pale. In some people, the breakdown of faulty red blood cells adds a slightly yellow tone.
5. A sore, smooth or swollen tongue
A red, smooth or sore tongue — sometimes called glossitis — along with mouth ulcers or a burning feeling in the mouth, can be an early clue.
6. Dizziness or balance problems
Low oxygen delivery plus nerve involvement can affect balance and coordination. Balance trouble is also a fall risk, so it is worth acting on quickly.
7. Mood changes
Irritability, low mood and anxiety have all been linked with low B12. These symptoms have many possible causes, so they are a reason to get checked, not a diagnosis on their own.
8. Heart palpitations or shortness of breath
When anemia is more advanced, the heart may beat faster to compensate. Chest pain or severe breathlessness needs same-day medical attention.

Early signs vs. later signs
| Stage | Signs | What it means |
|---|---|---|
| Early | Fatigue, mild brain fog, pale skin, sore tongue. | B12 stores are running low; anemia may be starting. |
| Developing | Tingling or numbness, dizziness, balance problems, mood changes. | Nerves and blood are both affected; get tested now. |
| Advanced | Difficulty walking, confusion, severe weakness, palpitations. | Nerve damage risk rises; needs prompt medical care. |
| Late / untreated | Lasting numbness, poor coordination, cognitive problems. | Some nerve damage may not fully reverse — early treatment matters. |
Who Is Most at Risk?
Some people are far more likely than others to run low on B12. If you belong to any of these groups, periodic testing is a reasonable conversation to have with your doctor — even if you feel fine.
- Adults over 50. Reduced stomach acid and intrinsic factor make this the largest at-risk group. The NIH states that deficiency affects 3% to 43% of older adults.
- People with pernicious anemia. An autoimmune condition in which the body destroys the stomach cells that make intrinsic factor. The average age of diagnosis is around 60, and it usually needs lifelong treatment, often by injection.
- People who have had stomach or weight-loss surgery. Procedures such as gastric bypass reduce both acid production and the absorbing surface of the gut.
- People with celiac disease or Crohn’s disease. Inflammation and damage in the small intestine reduce absorption.
- Vegans and strict vegetarians. B12 is found naturally only in animal foods. A plant-based diet without fortified foods or a supplement will almost always fall short over time.
- People taking metformin long term. Metformin can lower B12 levels; the effect is more likely the longer it is taken and the higher the dose.
- People taking acid-reducing medicines long term. PPIs and H2 blockers reduce the acid needed to free B12 from food.
- People with atrophic gastritis. Often silent, it reduces both acid and intrinsic factor.
If you are in two or more of these groups — for example, over 65 and taking metformin — your risk is higher still, and testing is even more worthwhile.
How B12 Deficiency Is Diagnosed
Diagnosis is a blood test, not a guess from symptoms — and that matters, because the symptoms of B12 deficiency overlap with dozens of other conditions, from thyroid problems to poor sleep to depression. The same fatigue and brain fog can also come from vitamin D deficiency, which is why testing matters. Your doctor will usually start with:
- A serum vitamin B12 blood test. This measures how much B12 is in your blood. MedlinePlus notes that normal values are roughly 200–900 pg/mL in many laboratories (around 300–1,050 pg/mL in the reference it cites), but ranges vary by laboratory, so your doctor interprets the number alongside your symptoms.
- A complete blood count (CBC). This can show the large red blood cells typical of megaloblastic anemia.
- A methylmalonic acid (MMA) test. The NIH describes MMA as the most sensitive marker of B12 status. When B12 is borderline — roughly 150–399 pg/mL — an MMA test helps confirm or rule out a true deficiency. MMA can also rise with reduced kidney function and with age, so it is interpreted in context.
- Sometimes a homocysteine test. B12 (along with folate and B6) helps keep homocysteine levels in check, so a high level can support the diagnosis.
One important caution: a “normal” B12 result does not always rule out deficiency if symptoms are present, and a low result does not always mean symptoms will follow. That is why doctors look at the full picture — symptoms, medicines, diet, other blood results and, when needed, MMA — rather than a single number. Do not start high-dose supplements just before a test without telling your doctor, because recent supplements can make the blood level look higher than your true body stores.
Best Food Sources of Vitamin B12
B12 occurs naturally only in animal foods. Plants do not make it, which is why fortified foods matter so much for people who eat little or no animal food. The values below are approximate, from the NIH Office of Dietary Supplements (based on USDA data). The adult recommended daily amount is 2.4 mcg.
- Clams, cooked (3 oz): about 84 mcg — the richest common source, far above a day’s need.
- Beef liver, cooked (3 oz): about 70 mcg — very high, but also high in cholesterol; an occasional food, not a daily one.
- Rainbow trout, cooked (3 oz): about 5.4 mcg — an easy way to cover the day’s need in one meal.
- Salmon, cooked (3 oz): about 4.9 mcg — also provides omega-3 fats.
- Beef, cooked (3 oz): about 2.4–6 mcg depending on the cut. Ground beef is lower than sirloin; check the label.
- Fortified breakfast cereal (1 serving): varies, often about 6 mcg — check the Nutrition Facts label, as fortification levels differ by brand.
- Milk (1 cup): about 1.2 mcg — dairy is a steady, everyday source.
- Yogurt (1 cup): about 1.1 mcg — a simple breakfast or snack source.
- Egg (1 large): about 0.6 mcg — modest, but it adds up across the day.
- Fortified nutritional yeast or plant milk: varies — useful for vegans, but only if the product is actually fortified; check the label.

A practical point: after 50, food alone may not be enough even when the diet looks good. The NIH advises people over 50 to get most of their B12 from fortified foods or supplements, because the B12 in those products is already in its free form and is absorbed more reliably when stomach acid is low. That does not mean food stops mattering — it means food plus a fortified food or a supplement is the safer combination for most people over 50.
Best Forms of Vitamin B12 Supplements
Walk into any pharmacy and you will see cyanocobalamin, methylcobalamin, hydroxocobalamin and adenosylcobalamin, in tablets, sublingual (under-the-tongue) tablets, sprays and injections. The marketing suggests one form is clearly better. The evidence does not.
The NIH states there is no evidence that absorption differs between the forms in supplements. Your body converts them all into the active forms it needs. What matters far more than the form is the dose, how consistently you take it, and whether your gut can absorb it at all.
- Cyanocobalamin: the most common, cheapest and most stable form; used in most multivitamins and fortified foods. Best for most people; the best-studied and best-value option. It contains a tiny amount of cyanide in the molecule — at supplement doses this is not a safety concern for healthy adults.
- Methylcobalamin: an active form the body uses directly. People who prefer an “active” form choose it; it works the same in practice. More expensive; less stable in storage; no proven absorption advantage.
- Hydroxocobalamin: a form often used for injections. Best for prescription injections, especially when B12 must be given by shot. Usually a prescription product, not a shop supplement.
- Adenosylcobalamin: the other active form used inside cells. Sometimes combined with methylcobalamin in “active B12” products. Little extra evidence over the standard forms.
Oral tablets vs. sublingual vs. injections
- Oral tablets (including high-dose 500–1,000 mcg). Even without intrinsic factor, about 1% of a large oral dose is absorbed by passive diffusion. That is why high-dose oral B12 can work even for some people with absorption problems — but only a doctor can judge whether it is enough for your situation.
- Sublingual tablets and sprays. Dissolved under the tongue. Popular and convenient, but there is no strong evidence they are absorbed better than swallowed tablets.
- Injections (usually cyanocobalamin or hydroxocobalamin). Given into a muscle, usually by a clinician. Needed when absorption is severely impaired — for example, pernicious anemia or after weight-loss surgery — or when deficiency is severe. Frequency is often monthly after an initial course; your doctor sets the schedule.
How to choose
- If you are over 50, eat normally and have no absorption problem: a standard supplement or a multivitamin containing B12 is usually enough. Cyanocobalamin is fine and is the cheapest option.
- If you take metformin or acid-reducing medicine: ask your doctor about testing and whether a dedicated B12 supplement (often 500–1,000 mcg) makes sense.
- If you have pernicious anemia, prior stomach surgery or severe deficiency: expect injections or high-dose oral treatment under medical supervision — a multivitamin will not be enough.
- If you are vegan or strictly vegetarian: take a reliable B12 supplement or eat fortified foods daily. This is not optional — B12 deficiency on a vegan diet is a matter of when, not if.
- Ignore “energy” claims. B12 supplements do not give extra energy to people whose B12 is already normal. If you feel more energetic after starting one, it is usually because a deficiency was corrected — not because B12 is a stimulant.
How Much B12 Do You Need After 50?
The recommended dietary allowance (RDA) for adults is 2.4 mcg per day. The NIH has not set an upper limit for B12, because no harm has been shown even at high doses — excess B12 is water-soluble and is usually passed in the urine. That does not mean “more is always better.” It means high-dose supplements are generally considered safe, but the right dose still depends on your blood level, your medicines and the cause of your low B12.
Practical guidance
- Maintenance (no deficiency, age 50+): 2.4 mcg from food and fortified foods, or a daily supplement of 25–100 mcg, or a larger weekly dose if your doctor prefers. Many multivitamins already contain 6–25 mcg.
- Mild deficiency or borderline levels: doctors commonly use 500–1,000 mcg daily by mouth, then recheck blood levels after a few months.
- Severe deficiency or absorption failure: injections or high-dose oral treatment as prescribed, with follow-up testing.
Recovery takes time. Energy often improves within weeks, but nerve symptoms can take months to improve — and damage that has been present for a long time may not fully reverse. That is the strongest argument for testing early rather than waiting for symptoms to become obvious. B12 does not work in isolation, either: magnesium, for example, supports energy production and muscle function, so if fatigue persists after B12 is corrected, it is worth asking your doctor whether other nutrients should be checked too.
Safety and interactions
- B12 is generally safe, with no upper limit set by the NIH.
- Tell your doctor about all medicines and supplements you take. B12 can interact with some medicines, and some medicines — metformin, PPIs, H2 blockers — lower B12. Certain antibiotics (such as chloramphenicol) can interfere with red blood cell production, and your doctor may want to know about them if B12 is being treated.
- Folate caution: taking large amounts of folic acid can mask a B12 deficiency by correcting the anemia while nerve damage continues. This is one reason a multivitamin or B-complex should not be used as a do-it-yourself substitute for a proper B12 check.
- Kidney disease: if you have reduced kidney function, MMA results and B12 dosing need a doctor’s interpretation.
Medicines and Conditions That Lower B12 — A Checklist for Your Next Appointment
Bring this list to your doctor or pharmacist and ask whether your B12 should be checked:
- Metformin (for type 2 diabetes or prediabetes)
- Proton pump inhibitors — omeprazole, lansoprazole, pantoprazole, esomeprazole
- H2 blockers — famotidine, cimetidine, ranitidine (where still used)
- Long-term use of antacids
- Weight-loss surgery or stomach surgery
- Celiac disease, Crohn’s disease or chronic gastritis
- Pernicious anemia or other autoimmune conditions
- A vegan or strict vegetarian diet
- Age over 65, especially combined with any of the above
Common Mistakes to Avoid
- Assuming fatigue is “just aging.” Fatigue has many causes, and B12 deficiency is one of the most treatable. A blood test is cheap and simple — do not guess.
- Starting a high-dose supplement before testing. It can raise your blood B12 and make the test harder to interpret. Test first, then supplement — unless your doctor advises otherwise.
- Choosing a supplement by form instead of by dose. Methylcobalamin is not proven better absorbed than cyanocobalamin. Spend the difference on a product from a reputable brand instead.
- Relying on a multivitamin when you have an absorption problem. A standard multivitamin contains a small B12 dose that may not be enough if you cannot absorb it.
- Treating memory problems with B12 without a diagnosis. B12 has not been shown to prevent or treat dementia in people with normal B12 levels. Memory changes always deserve a proper medical evaluation.
- Ignoring tingling or balance problems. These are the symptoms most likely to become permanent if left untreated. They are not something to “watch for a few months.”
- Stopping metformin or acid-reducing medicine on your own. Never stop a prescribed medicine to fix B12. Ask your doctor about monitoring and supplementation instead.
- Trusting “B12 energy” marketing. B12 is not an energy drink. It restores normal function when you are deficient; it does not supercharge a healthy body.
A Simple 4-Week Plan to Protect Your B12 After 50
- Week 1: Book a B12 blood test with your doctor, especially if you are over 60, take metformin or acid-reducing medicine, or have any symptoms. Bring your medicine list.
- Week 2: Review your diet: add a B12-rich food or a fortified food each day (for example, an egg at breakfast, yogurt as a snack, fortified cereal, or fish twice a week).
- Week 3: If your doctor recommends a supplement, start it as directed — same time each day, so it becomes a habit. Keep the bottle where you will see it.
- Week 4: Note how you feel (energy, sleep, tingling) in a short diary, and book the follow-up blood test your doctor advised. Share the diary at the appointment.
Small, steady steps beat a single dramatic change. B12 status improves over weeks and months, not overnight.
When to See a Doctor
See your doctor promptly if you notice:
- Persistent fatigue or weakness that does not improve with rest
- Tingling, numbness or loss of balance
- Memory problems, confusion or mood changes that are new
- A sore tongue, mouth ulcers or unexplained pale skin
- Shortness of breath or heart palpitations
Seek same-day medical care for chest pain, severe breathlessness, sudden weakness on one side of the body, or a fall caused by dizziness or balance loss. These can signal something more urgent than B12 deficiency.
Frequently Asked Questions
1. How much vitamin B12 should a person over 50 take daily?
The adult RDA is 2.4 mcg per day. Because absorption falls with age, the NIH recommends that people over 50 get most of their B12 from fortified foods or supplements. Many doctors suggest a daily supplement of 25–100 mcg for maintenance, or 500–1,000 mcg if levels are low — but the right dose depends on your blood level and health situation, so ask your doctor.
2. What is the first sign of B12 deficiency?
Fatigue and weakness are usually the first signs, often with mild brain fog. Tingling in the hands or feet, a sore tongue and pale skin can also appear early. Because these symptoms develop slowly and overlap with normal aging, they are frequently missed.
3. Is methylcobalamin better than cyanocobalamin for seniors?
No — there is no good evidence that one form is absorbed better than the other. The NIH states that absorption does not differ by form. Cyanocobalamin is the most studied, most stable and cheapest option. Choose based on dose and reliability, not on the form name.
4. Can B12 deficiency cause memory loss?
Yes, low B12 can cause memory problems, confusion and difficulty concentrating that can look like dementia — and correcting a deficiency can improve them. However, B12 supplements have not been shown to prevent or treat dementia or Alzheimer’s disease in people whose B12 is already normal. Memory changes always need a proper medical evaluation.
5. Does metformin lower vitamin B12?
Yes. Metformin can lower B12 levels, especially with long-term use and higher doses. If you take metformin, ask your doctor about periodic B12 testing. Never stop metformin on your own.
6. How is B12 deficiency diagnosed?
Usually with a blood B12 test plus a complete blood count. If the B12 result is borderline (roughly 150–399 pg/mL), doctors often check methylmalonic acid (MMA), which the NIH describes as the most sensitive marker of B12 status.
7. Can you get enough B12 from food alone after 50?
Sometimes, but often not reliably. The NIH advises people over 50 to get most of their B12 from fortified foods or supplements because stomach acid — needed to free B12 from food — declines with age. Food plus a fortified food or supplement is the safer combination.
8. How long does it take to recover from B12 deficiency?
Energy and blood counts often improve within weeks, but nerve symptoms such as tingling or balance problems can take months. If deficiency has been present for a long time, some nerve damage may not fully reverse — which is why early testing and treatment matter so much.
Conclusion
Vitamin B12 after 50 is a story about absorption, not appetite. Your stomach makes less acid, intrinsic factor can decline, and medicines such as metformin and acid reducers add to the problem — so even a good diet may not be enough. The early signs (fatigue, brain fog, tingling, a sore tongue, pale skin) are easy to mistake for aging, but they are also easy to check: a simple blood test, and an MMA test when the result is borderline, can settle the question. Food, fortified foods and supplements all have a role, and the form on the label matters far less than the dose and whether your body can absorb it.
If you are over 50, take metformin or an acid-reducing medicine, eat a plant-based diet, or have noticed any of the signs in this guide, bring it up at your next appointment — and if you have tingling, balance problems or memory changes, do not wait for the next routine visit. A short conversation and a blood test could prevent problems that are much harder to undo later.
Next step: Share this guide with a parent, partner or friend over 50 who takes metformin or an acid-reducing medicine, and ask your doctor whether a B12 test belongs on your next check-up list.
This article is general information only and is not medical advice. It does not replace a conversation with your own doctor or pharmacist. Always talk to a healthcare professional before starting, stopping or changing any supplement or medicine.
Sources
- NIH Office of Dietary Supplements — Vitamin B12, Fact Sheet for Consumers: https://ods.od.nih.gov/factsheets/vitaminb12-consumer/
- NIH Office of Dietary Supplements — Vitamin B12, Fact Sheet for Health Professionals: https://ods.od.nih.gov/factsheets/VitaminB12-HealthProfessional/
- MedlinePlus — Vitamin B12 (Medical Encyclopedia): https://medlineplus.gov/ency/article/002403.htm
- MedlinePlus — Vitamin B12 deficiency anemia: https://medlineplus.gov/ency/article/000574.htm
- MedlinePlus — Vitamin B12 level (blood test): https://medlineplus.gov/ency/article/003705.htm






3 Comments